Hello Reno Families!


Hello, I am  Leslie Greenberg.  I am a family physician in Reno, Nevada.  I attended Northwestern University in Chicago, then University of Nevada School of Medicine.  I relocated back to my hometown in 2015.  I trained and practiced medicine in the Midwest (Indiana and Kansas) for 20 years before moving back West.  I consider myself a teacher and educator.  I  have taught 450 + family medicine residents (and countless medical students), over nearly 30 years.  I currently teach at the family medicine residency program in Reno and also see private patients.  I care for newborns through elderly patients in both the hospital and office.  I love to do women’s health (contraception and menopause care) and procedures: skin biopsies, circumcisions, IUD insertion/removals, paps, colposocopies, and toenail removals. I am a Menopause Society certified physician.  I invite you to read my blog.  If you would like to become a patient, please call 775-982-1000.

Medical Disclaimer

Please remember that medical information provided by myself, in the absence of a visit with a health care professional, must be considered an educational service only.  This blog should not be relied upon as a medical judgement and does not replace a physician’s independent judgement about the appropriateness or risks of a procedure or condition for a given patient.  I will do my best to provide you with information that may help you make your own health care decisions.


Posted in Uncategorized | Comments Off on Hello Reno Families!

No-cost genetic screening through a research project in Reno!

As a family medicine physician in Reno, I have the opportunity to work with the Healthy Nevada Project, an innovative community health research program powered by Renown Health. I like to tell my patients that we cannot change your genes, but we can check them to see if you have a gene mutation (since birth!) that can increase your risk of cancers or cardiovascular issues. If you have a gene mutation, then we can watch you in a whole different way. We can find issues when they are small and let you live your one, big, beautiful life.

The project is designed to better understand how genetics, health history, and environmental factors influence health outcomes while giving participants useful information that may help guide their own care.

Adults age 18 and older who qualify can receive no-cost genetic screening for several important hereditary conditions, including Hereditary Breast and Ovarian Cancer Syndrome, Lynch Syndrome, and Familial Hypercholesterolemia. These conditions are especially important because identifying a genetic risk can allow patients and their healthcare providers to consider earlier screening, preventive strategies, and more personalized care.

The Healthy Nevada Project would like to continue enrolling new participants in genetics research and currently needs our help reaching approximately 12,000 additional patients by the end of December. If you are in Northern Nevada you can go to HealthyNV.org and sign up!

Participants receive genetic sequencing through Helix, which provides screening for some of the most common actionable hereditary cancer and cardiovascular risks. Their genomic sequencing is also retained securely through Helix, creating the potential for additional genetic testing in the future, including expanded hereditary cancer panels and pharmacogenomic testing when clinically appropriate.

As a primary care physician, I believe programs like this represent an exciting step toward more personalized medicine. Genetic information does not replace good clinical care, but when used thoughtfully, it can help us identify risk earlier and make more informed decisions with our patients.

Sign up at HealthyNV.org today!

Posted in Uncategorized | Tagged , , , , , , , , , , , , , , , , , , , , , , , | Leave a comment

Should Vitamin K shots be given to newborns?

Healthcare professional administering an injection to a newborn in a hospital bassinet
A healthcare professional carefully administers an injection to a newborn in a hospital bassinet.

As a family medicine physician, I routinely see newborns in the hospital during those first precious hours and days before they go home. One of the routine treatments I strongly recommend is the vitamin K injection given shortly after birth. Vitamin K is not a vaccine, it is a vitamin that is low in newborns. Oral Vitamin K does not work well, it is best given as a shot.

Newborns naturally have very low vitamin K stores. Vitamin K is essential for normal blood clotting, and without enough of it, babies can develop vitamin K deficiency bleeding, or VKDB. This bleeding can occur in the first days of life or, more concerningly, weeks to months later. Late VKDB can involve bleeding into the brain, and approximately 30% to 60% of infants who develop late VKDB have intracranial bleeding. Intracranial bleeding can cause developmental delays, inability to speak, feed or walk, or death.

A large recent U.S. study helps put this risk into perspective. Researchers studied 5,240,780 infants born between 2017 and 2025. Of these babies, 234,825 did not receive the recommended intramuscular vitamin K injection.

Babies who did not receive vitamin K had a significantly higher risk of bleeding during the first six months of life: 288 bleeding events per 10,000 infants compared with 186 per 10,000 among babies who received vitamin K. After adjustment for other factors, the risk of bleeding was 47% higher.

The difference was even more striking for bleeding in the brain. Infants who did not receive vitamin K had more than twice the risk of intracranial bleeding—33 versus 13.2 cases per 10,000 infants. They also had a higher rate of death accompanied by bleeding during the birth hospitalization.

When I discuss vitamin K with new parents, I understand that every medication given to a newborn deserves thoughtful consideration. But this is a simple preventive treatment that has been given for decades with an important purpose: protecting babies from a rare but potentially devastating and preventable bleeding disorder.

When my babies were born, they all received Vitamin K. Please know that physicians give their loved ones Vitamin K.

Posted in Uncategorized | Tagged , , , , , , , , , , , | Leave a comment

Measles immunity gap for children.

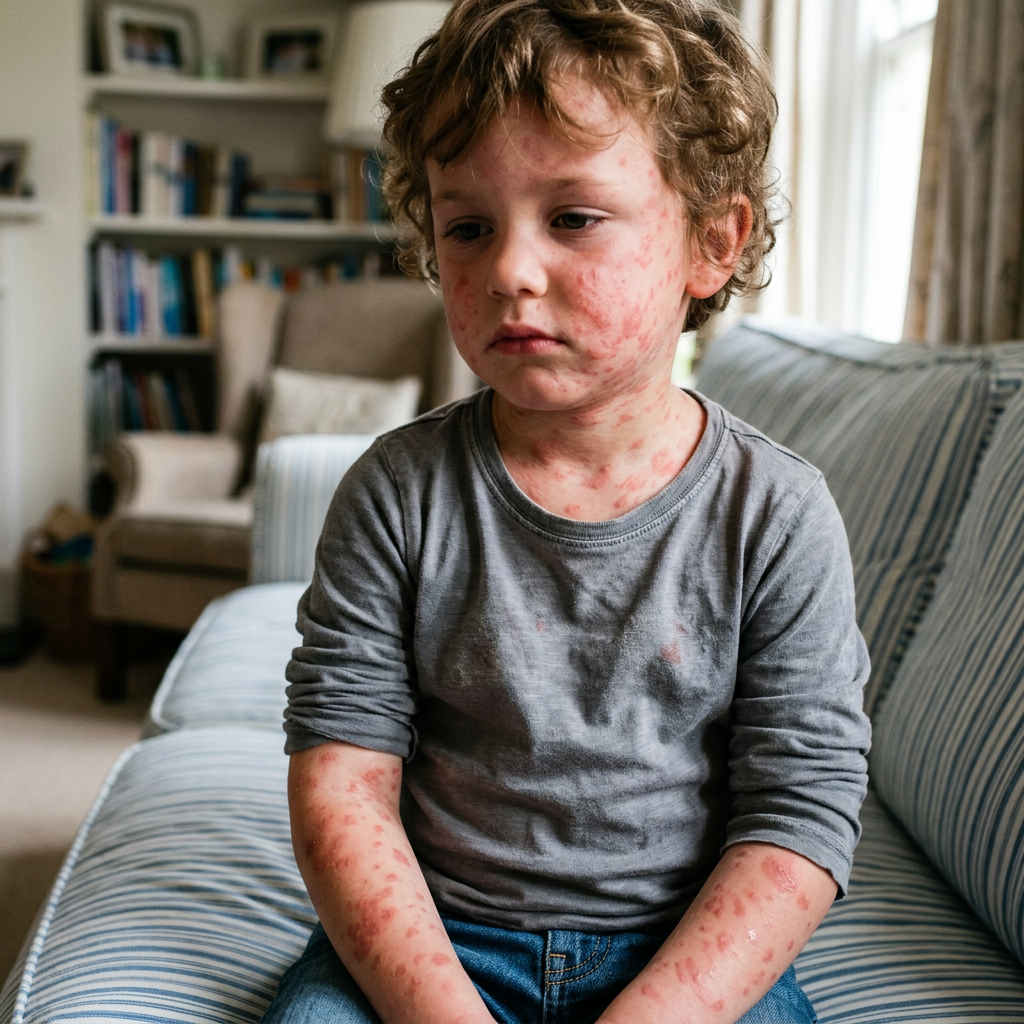
Child sitting on sofa with widespread red skin irritation
A child sits quietly on a sofa with widespread visible skin irritation on the face, neck, and arms.

As a family physician who cares for children both in the hospital and the office, I spend a lot of time talking with parents about vaccines—what vaccines we give, when we give them, and why timing matters. New research about measles highlights an important period of vulnerability for our youngest patients.

The first routine dose of the measles, mumps, and rubella (MMR) vaccine is recommended at 12–15 months of age. Until then, we have historically relied in part on antibodies passed from mother to baby during pregnancy to provide some protection early in infancy.

But that protection may disappear sooner than many parents realize.

A recent U.S. analysis presented at IDWeek found that by six months of age, most infants no longer had detectable levels of maternal neutralizing antibodies considered protective against measles. Researchers found that antibody levels declined rapidly during the first months of life and, by six months, median levels had fallen below the study’s threshold for protection across the measles strains studied.

That creates what I think of as an immunity gap: a period between roughly six months and the routine MMR vaccination at 12 months when an otherwise healthy infant may have little protection against measles.

This matters more now because measles is circulating much more widely in the United States. As of October 22, 2026, the CDC had reported 4,588 confirmed U.S. measles cases THIS year.

Parents who vaccinate their children on schedule are doing exactly what we ask them to do. Yet an infant who is simply too young for the routine vaccine can still be exposed when measles spreads in the community. That is one reason high vaccination rates among older children and adults are so important: vaccination protects not only the person receiving the vaccine, but also babies who are not yet old enough to receive their routine first dose.

There is an important exception to the usual schedule. The CDC recommends that infants 6–11 months old receive an early MMR dose before international travel, and local public health authorities may recommend an early dose during certain measles outbreaks. An MMR dose given before the first birthday does not replace the routine series; those children still need two subsequent doses beginning at 12 months.

For parents of young infants, the takeaway is do not panic, but be aware. Keep everyone in your household appropriately vaccinated, pay attention to local outbreaks, and talk with your physician before travel or if you believe your baby may have been exposed to measles.

Posted in Vaccines | Tagged , , , , , , , , , | Comments Off on Measles immunity gap for children.

Emergency Poison Control for Young Kids: Quick Guide

Young children sometimes swallow medicine, cleaning products, vitamins, or other household items. This is especially common when they start walking (and medications and solvents are not put away out of arms reach) or when at a home that is not theirs.

A new study, “Assessing unnecessary emergency department visits for poison exposures in pediatric patients less than six years old,” found that many suspected poisonings in children under age 6 may not require an emergency room visit.

• 38% clearly did not need ER care.

• 27% were unlikely to need ER care.

If your child may have been exposed to something harmful, call Poison Control at 1-800-222-122 Poison specialists are available 24 hours a day, 7 days a week, including holidays. The call is free.

They can help you decide whether your child can be safely watched at home or needs emergent medical care.

Of course, call 911 right away if your child has trouble breathing, has a seizure, collapses, or cannot be awakened.

A good tip: save 1-800-222-1222 in your phone now, before you need it.

I hope this helps.

Posted in medication issues, Pediatrics, safety, toxin | Tagged , , , , , , , , , | Comments Off on Emergency Poison Control for Young Kids: Quick Guide

Testosterone therapy for women?! A webinar today!

As a long-time physician who is also Menopause Society Certified (MSCP), here is a great FREE virtual resource for women to learn about testosterone, https://www.fda.gov/…/fda-public-meeting-testosterone…

Join the FDA’s Office of Women’s Health and Center for Drug Evaluation and Research for a free public workshop on Testosterone Use in Menopausal Women on September 17th.

Experts will discuss the current scientific evidence and critical knowledge gaps surrounding testosterone use in menopausal women to help inform future research and potential drug development in this important area of women’s health. Registration is required for both in-person and virtual attendance, and you can also submit your public comments directly to the FDA by Oct.19. For more details visit: . #WomensHealth#Menopause#HormoneTherapy

See less

Posted in Uncategorized | Tagged , , , , , , , , , , , | Comments Off on Testosterone therapy for women?! A webinar today!

Cervical Cancer Screening: Protect Your Health Today

Have You Had Your Cervical Cancer Screening?

As a family physician, I am seeing that more women are falling behind on cervical cancer screening. Screening tests are meant to help you lead a fuller, more healthy life. It takes a minute to get a pap smear done. Ask your physician to add it to your annual well visit.

A recent study found that by 2023, almost 1 in 3 women ages 21 to 29 had never been screened for cervical cancer. In 2005, that number was about 1 in 8.

Screening is important because it can find changes in the cervix before they turn into cancer. Cervical cancer is one of the cancers we can often prevent with regular screening.

Depending on your age and health history, screening may include a Pap test, an HPV test, or both. These tests are usually quick and can be done during an office visit.

You may still need cervical cancer screening even if you:

  • Feel perfectly healthy
  • Have no symptoms
  • Have not had sex recently
  • Have gone through menopause

If you are not sure when your last Pap or HPV test was, ask your doctor. We can look at your records and help you figure out when your next screening is due.

Don’t Forget the HPV Vaccine

The HPV vaccine can lower your risk of HPV infections that can lead to abnormal cervical cells, cervical precancer, and cervical cancer.

The CDC recommends HPV vaccination for everyone through age 26 if they have not already completed the series. For adults ages 27 through 45, vaccination may still be helpful for some people and can be discussed with your physician.

If you have not had all of your HPV vaccine doses, ask your doctor whether you should finish the series.

The most important message: Don’t wait for symptoms. Cervical cancer screening and HPV vaccination are two important ways to help prevent cervical cancer.

Posted in pap test, Women's Health | Tagged , , , , , , , , | Comments Off on Cervical Cancer Screening: Protect Your Health Today

How COVID-19 Vaccines Reduce Hospitalizations and Deaths

As a family physician, I see patients daily that are hesitant to get vaccines. This “vaccine hesitancy” is getting more profound. Patients are even more hesitant to get the Covid vaccine. As an academic faculty physician, I read (good reliable) research all the time.

I get my covid and flu vaccine at the same time every fall (and have done this since the pandemic). Research has shown that getting both vaccines does not decrease the immune response to either vaccine. It you are prone to feeling ill after a vaccine, you may have this same response when you get both the flu and covid vaccine. This research shows that the Covid vaccine significantly decreases the risk of getting very sick or needing hospitalization from the covid infection or dying from covid.

In the era of Omicron, previous vaccinations, and previous infections, do COVID-19 vaccines still provide a clinically important benefit?5COVID-19 vaccines still reduce emergency department visits, hospitalizations, and mortality.

COVID-19 vaccines remained effective at reducing emergency department visits, hospitalizations, and deaths in this high-quality observational study. Vaccine effectiveness is similar to earlier randomized trials, with a 39% reduction in hospitalization and a 64% reduction in mortality.
Posted in Uncategorized | Tagged , , , , , , , , | Comments Off on How COVID-19 Vaccines Reduce Hospitalizations and Deaths

Should male sex partners of women with bacterial vaginosis get treated?

Clinical questionBottom-line answer
Does treatment of the male sex partner reduce the likelihood of recurrent bacterial vaginosis in women?3Oral and topical treatment of male sex partners of female patients with bacterial vaginosis reduces recurrence.

Treating male sex partners of women with bacterial vaginosis with oral metronidazole and topical clindamycin decreased the likelihood of recurrence (number needed to treat = 3). Ensuring adherence to the regimen is key; these results were achieved despite only 47 of 80 male partners being at least 70% adherent to the protocol.

Yes! New research suggests that treating male sexual partners may help reduce the chance of bacterial vaginosis (BV) coming back.

Many women with BV notice a “fishy” odor, especially after sex, although some women have few or no other symptoms.

Recent studies have found that when male partners are treated at the same time—with oral metronidazole and topical clindamycin—the risk of BV recurring may be lower. This is an important shift in how we think about recurrent BV and suggests that treating both partners may help some couples break the cycle of repeat infections.

This new treatment of male-partner treatment stems from a 2025 randomized trial (Vodstrcil et al., NEJM) which found that concurrent treatment of male partners in monogamous heterosexual couples significantly reduced recurrence in women. This new treatment option challenges the longstanding practice of treating women alone. This contrasts with older guidance (and prior negative trials without topical therapy) that partner treatment was not beneficial; the difference is attributed to clearing penile carriage with topical antibiotics. 

I hope this helps!

Posted in General Medicine- Adults, Male issues, Women's Health | Tagged , , , , , , , , | Comments Off on Should male sex partners of women with bacterial vaginosis get treated?

The Investment That Helps Nevada Keep More Doctors…

Want to learn more? Read on. https://www.2news.com/news/local/nevada-awards-nearly-16-million-to-expand-physician-training-programs/article_42d1831f-1c6a-4431-b4ff-95853d3126dc.html

Posted in Uncategorized | Tagged , , , , , , , , , | Comments Off on The Investment That Helps Nevada Keep More Doctors…

Understanding Estradiol Levels for Bone Health

As a Menopause Society Certified Provider, I stay current with research and regularly attend webinars and conferences. There are many expert researchers and physicians discussing whether there is any need to check estradiol levels.

This is in response to online forums stating that estradiol levels of 80–100 pg/mL are needed for bone protection. According to hormone researcher Dr. Sue Davis, this is “nonsense and not evidence-based.” This misinformation is based on an older study. The way estradiol is measured today is different, and laboratory assays may be affected by other circulating hormones. Additionally, if a woman is taking oral estrogen, a significant amount is converted to estrone, which is not reflected by a standard estradiol level.

What strength of estradiol patch helps decrease bone loss?
An estradiol patch delivering as little as 14 mcg/day helps decrease bone loss. A 50 mcg/day patch has been shown to stop bone loss in approximately 95% of women.

What is the best dose of estrogen for women?
Truly, the most effective dose of estrogen for peri- or menopausal women is the dose needed to adequately relieve menopausal symptoms.

Will increasing the estrogen dose help more (result in less bone loss) than a lower dose?
Not all bone loss is due to low estrogen levels. Bone loss is multifactorial and may be influenced by genetics, physical activity, nutrition, and adequate protein intake. Estrogen is not a silver bullet for preventing bone loss. Simply increasing a woman’s estrogen dose does not assure additional bone protection.

The online chatter is not supported by the best available scientific evidence.

To sum this up, bone is exquisitely sensitive to even low doses of estradiol. Routine estradiol blood levels are generally not helpful for determining bone protection. As I often say, more does not necessarily mean better.

I hope this helps.

Posted in Uncategorized | Tagged , , , , , , , , , , , , | Comments Off on Understanding Estradiol Levels for Bone Health