Embarrassed about your pale pasty skin? Get over it.

Wanting a rich, deep tan?  Frequenting a tanning salon?. . . Please don’t.  May has been designated Melanoma/Skin Cancer Detection and Prevention Month.  So, let’s celebrate our natural skin color, whatever color it is.

American Academy of Dermatology did an online study of 3800 (adolescent through mid 20s)  females.  The results are shocking!

81% of respondents had tanned outdoors “frequently or occasionally” in the past year.  32% used a tanning bed in the past year, while 25% reported using a tanning bed at least weekly. 

The SAFE alternative to UV-exposure, a “spray tan,” was NOT used by  86% of said respondents in the past year.  The 18- to 22 year-old female crowd is nearly twice as likely (40%)  to use indoor tanning beds as compared to 14- to 17- year olds (22%).   Cost?  Transportation issues?

There are more tanning salons than Starbucks or McDonalds.  In a recent survey in 116 U. S. cities, on average there are 42 tanning salons per city. 

Teens and early adults may not appreciate the consequences of the cumulative sun exposure.  Nearly 75% of skin cancer deaths are from melanoma with rates rising for the last 30 years.

The World Health Organization declared UV radiation from the sun and artificial light sources a known carcinogen (cancer-causing agent) and called for prohibiting minors from indoor tanning. 30 + states either prohibit or require parental consent for minors who want to use indoor tanning devices.

So, consider stopping the “fake bake,”  instead buy sunscreen, embrace your natural skin color, and see your doctor for  a skin check.

Hope this helps.

Posted in Dermatology, Dermatology, General Medicine- Adults, Pediatrics, safety, Uncategorized | Tagged , , , , , , , , , , , | Comments Off on Embarrassed about your pale pasty skin? Get over it.

Head lice (Is your skin crawling?). Two new treatments.

Good people get head lice.  It is especially rampant in schools where coats may hang next to each other (and the lice essentially jump from one household to another).  Head lice are becoming more resistant to over-the-counter rinses.  There are two reasonably effective therapies to kill the head lice.  Both are non-pesticide and non-neurotoxic therapies that asphyxiate the Pediculosis humanis capitis.  Ick!

  • Ulesfia lotion.  It’s a benzyl alcohol/mineral oil product that stuns the lice spiracles (breathing holes) so the lice drown in the mineral oil vehicle.  (Too much information?)  It can be used in patients older than 6 months.  It needs to be used in a quantity to fully saturate the hair.  Rinse after 10 minutes.  It may not kill the eggs, so repeat one week later.
  • Cetaphil gentle skin cleanser.  Cetaphil is applied to hair and scalp.  2 minutes later comb (not wash) out.  Eight hours later the hair is washed with regular shampoo.  This treatment is repeated once weekly for 3 weeks.

Cure rates for either treatment is 85-97%.  Clothes and bedding should be heated in a hot dryer for 10 minutes and combs washed in isopropyl alcohol for 10 minutes.

Other home remedies like mayonnaise, olive oil, butter, Vaseline, and vinegar were not found to be nearly as effective.

Hope this helps.

Posted in General Medicine- Adults, Pediatrics, Uncategorized | Tagged , , , , , , , , , | Comments Off on Head lice (Is your skin crawling?). Two new treatments.

Teens birthing babies tumbles to a record low.

This is something to celebrate!  As a mother, I know that once you have a child your life (and your life’s pathway) are forever altered.  And, you are forever tied to their father (hi, honey!).   My teen patients and I discuss what is happening to their bodies and decisions they will be making.  Dating?  Boundaries?  Sex?  Contraception?  STDs?  Pregnancy?  I have rarely had a parent that did not want me to be a professional sounding board for their changing teen.

The CDC released data that the teen birth rate has fallen 37% over the last 20 years.  However, our rate of teen pregnancy (ages 15-19) is still NINE times higher than in many other developed countries.   The numbers of teens having sex decreased in white, black and Hispanic races for both boys and girls, but black and Hispanic girls remain twice as likely (as white girls) to become teenage mothers.

A CDC fact sheet states that health care providers can help reduce the teen birth rate.  My role is to listen, counsel, and help anyway that I can.  Use your family physician to help educate your children about the adult decisions they will face.

Hope this helps.

Posted in contraception, infections, Obstetrics, Pediatrics, safety, Uncategorized, Women's Health | Tagged , , , , , , , , , | Comments Off on Teens birthing babies tumbles to a record low.

Happy Mother’s Day to all the mothers and those WITH mothers. . .

What a special day!  A time for us to  thank our mothers, reflect on our childhoods, and for those of us who are mothers. . . to savor our children.  I am blessed with three children and am amazed by their unique constellation of personality traits, quirks and talents. 

I chose  the career of “family medicine with obstetrics” because it is energizing, engrossing, emotional and truly amazing.  I considered obstetrics during medical school, but I wanted to keep following  the mother and baby.  I counsel  couples  through their pregnancy and am present to help with the birth of  their baby and becoming a family.  Those first few weeks of a newborn’s life are so challenging to the new parents.  I love to hold their hands, answer the lists of questions.  It is a delight and an honor. 

Rajneesh says “The moment a child is born, the mother is also born.  She never existed before.  The woman existed, but the mother, never.  A mother is something absolutely new.”  Well said.

How fantastic.  Enjoy what you have.  Revel in your life.

Happy Mother’s Day to all.

Posted in Uncategorized | Tagged , , , , , , , , , , | Comments Off on Happy Mother’s Day to all the mothers and those WITH mothers. . .

Should I insist my doctor order an MRI?

There are lots of magazine articles telling patients that if they want better care to speak up for themselves!  This brings up . . . are MRIs done too often? 

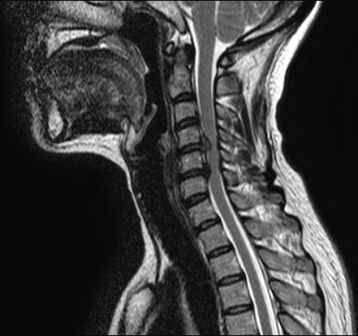
Magnetic Resonance Imaging has become a routine test in the evaluation of musculoskeletal conditions.   Most patients with neck, back, knee or shoulder pain will improve with conservative management.  MRI often shows pathology (aka that something is wrong)  that may have no relationship to the patient’s symptoms.  Tests have shown that young and middle-aged people with NO symptoms 30-40% of the time have changes in their disks.    The MRI can give confusing information that may not identify the source of pain. 

To optimize healing, I do a thorough history and physical exam.  Certainly, if there are “red alarms” like infection or acute disc herniation or cauda equina syndrome, then an MRI is warranted.   If conservative therapy does not help resolve the problem in 4 to 6 weeks, then an MRI may help also.  We physicians are trained to not obtain tests that won’t help the diagnosis or plan of care.  MRI is not indicated if the result will not alter treatment.  Muscle stretching and strengthening are the cornerstones of rehabilitation.  That requires the patient be motivated and engaged in therapy. 

cervical spine MRI

Hope this helps.

Posted in bone health, General Medicine- Adults, Uncategorized | Tagged , , , , , , , , , | Comments Off on Should I insist my doctor order an MRI?

Are you considering NOT immunizing your child?

A new position statement was released revealing that even a small number of unimmunized individuals can greatly increase spread of disease.  For children who do NOT get immunized, their risk of measles is 35 times those who are vaccinated, 23 times for whooping cough and 9 times for chicken pox.  If an unimmunized child contracts an infection, they may infect your incompletely immunized child, too.  Read more. . .

Pediatric Infectious Diseases Society Rejects ‘Personal Belief’ Immunization Exemptions — AAFP News Now — American Academy of Family Physicians.

Posted in infections, Pediatrics, Uncategorized, Vaccines, Vaccines | Tagged , , , , , , , , , , | Comments Off on Are you considering NOT immunizing your child?

Did your pedicure give you an infection?

I was teaching physicians the other day and helped take off a pus-filled, red and angry  ingrown toenail.  This is immensely rewarding.  When the toenail digs into the skin folds on the feet and every step causes pain, we physicians can help.

Ingrown toenails occur when the nail grows downward on the sides (especially of the big toe) and inflames the skin around the nail border.  This may happen because of trauma (like a stubbed toe), but it more commonly is caused by trimming the sides of the toenail too much.  If it is only mild, soaking the toes for 15 minutes three times a day for 2 weeks may help. After the soak, gently nudge the skin surrounding the nail away from the nail.  Wedging a toothpick or dental floss under the corner of the nail that is imbedded in the skin may help elevate it and relieve the problem.  Epsom salts can be placed in the water, if desired (your feet will be softer, too!)  Your doctor can prescribe a high potency steroid cream to help decrease the inflammation in the tissue.

If this does not help, or there’s a raging  pain/infection, we can take that part of the toenail off.  Your physician will

  • numb the toe with a digital block which will feel like a pinch on both sides of your toe.  That’ll make your entire toe numb.
  • remove a portion of the toenail so that it may regrow in the correct manner.  This new nail should not be trimmed until it is even with the end part of the nail.
  • An antibiotic ointment may be suggested by your physician on the bare nailbed until the nail has started to grow.
  • Oral antibiotics have not been shown to decrease the recovery time.

Like I tell my kids. . . let’s cut those toenails straight across.  Not angled like the fingernails.

Hope this helps.

Posted in foot health, General Medicine- Adults, infections, Uncategorized | Tagged , , , , , , , , , | Comments Off on Did your pedicure give you an infection?

What to do about molluscum?

I had a conscientious mom “up in arms” about her daughter having two molluscum lesions on her neck. I calmed her a bit and then discussed the treatment options with her. . .

Molluscum is a poxvirus causing a chronic localized infection.  The lesions are firm, flesh-colored, and dome-shaped.  It is considered common, with 5% of US children having molluscum.  Those with eczema may get molluscum easier.  Molluscum also affects healthy adolescent and adults, often from sexual contact or contact sports.

The poxvirus transmits from skin-to-skin, although it has been shown to transmit by towels or sponges and, rarely, in pool water. Humans are the only host and takes usually 2 to 6 weeks from contact until first lesion forms. In sexually active adolescents or adults, STD screening should also be performed.

There is a decision to make: to treat or not.  Adolescents and adults should be treated so as to avoid spread.  But for children, we can advise that molluscum is not harmful and will go away on its own (although this will take months.) A systematic review in 2009 showed “insufficient evidence to conclude that any treatment was definitively effective.”

That means that I do not push children to have treatment.

I do offer the following. . .

  • Cryotherapy otherwise known as (“freezing”). Cons: painful to young children, may cause scarring and decreased skin pigmentation where frozen.
  • Curettage (scooping out the dome-shaped lesion). Pros: 80% worked after a single session. Cons: fails more often with more lesions and with a history of eczema, may cause small depressed scar
  • Cantharidin (a liquid blistering agent). Requires skill of physician placing the liquid. Repeat applications every 2 to 4 weeks commonly needed. Can cause scarring.

To avoid spread, cover lesions with clothing or bandages while at sleepovers and during contact sports.

To treat or not to treat? That is the question. . .

Posted in Dermatology, Dermatology, General Medicine- Adults, infections, infections, Pediatrics, Sexually Transmitted Infections, Uncategorized | Tagged , , , , , , , , , , | Comments Off on What to do about molluscum?

Should we be facebook friends?

Social networking and doctoring.  Interesting concepts.  USA Today’s opinion editorial from a physician backs up the idea that doctors should not be “friending” their patients.    Her reasons were two-fold. . .

Professional judgment may be impaired when a physician has another relationship (financial, social or professional) in addition to the therapeutic relationship.  As a family doctor in a tight-knit community, I am friends with many of my patients.   I try to keep these relationships separate and distinct. 

There is also the issue that in a public platform, such as facebook, there’s threat to patient privacy.  The American Medical Association adopted a social media use policy November 2010.  It states that physicians “should be cognizant of standards of patient privacy and confidentiality that must be maintained in all environments, including online, and must refrain from posting identifiable patient information online.”  I appreciate that.   I once replied to a patient’s facebook question regarding morning sickness and “outed” her pregnancy to her extended family.

My patients know how to reach me during the day and  after hours.  I am accessible.  Online is not a good  forum.  I liken online correspondence  to a “curbside consult.”  When I’m at a BBQ and a patient asks me about an issue  (hip pain, vaginal discharge—you’d be surprised. . .) I do not have access to past medical history, allergies, surgeries, test results nor can I do an adequate physical exam.  That is subpar health advice.  An office visit is the best way to conscientiously and thoroughly address health problems. 

Hope this helps.

Posted in Uncategorized | Tagged , , , , , , , , , | Comments Off on Should we be facebook friends?

What to do if you think you have shingles. . .

If you’ve had chicken pox, the herpesvirus is hibernating in your body.  It can reactivate anytime and cause shingles.   Shingles is a painful , itchy, burning, bugs-under-your-skin-feeling rash on one side of the body.  See your doctor for confirmation.

The goals of antiviral therapy are not to get rid of the virus (as this is impossible) but instead to promote faster healing of skin lesions, lessen the severity and duration of pain, and to decrease the incidence or severity of postherpetic neuralgia (which means post-herpes-nerve-pain at the same site of the rash).

Antiviral medication is recommended for patients >50 years of age with uncomplicated shingles.  The patient needs to see the doctor within 72 hours of clinical symptoms or medication may not help decrease the pain or shorten the course.   Two antiviral choices are Valacyclovir (1000 mg three times daily for seven days)or acyclovir (800 mg five times daily for seven days).  Both are effective, acyclovir is much less expensive but less conveniently dosed.

The benefit of antiviral therapy in younger patients (under 50) is not as clear, as younger patients are less likely to have post herpetic neuralgia.   But, because antivirals are relatively safe, they CAN be given if the patients are diagnosed within 72 hours of clinical symptoms.

In short. . .

  • Anyone who has had the chicken pox can get shingles.  Be aware of feelings of skin tingling, burning and then a rash developing.  See your doctor.
  • Shingles nerve pain hurts.  Your doctor can prescribe pain medication.
  • Early antiviral treatment for shingles reduces the duration and incidence of postherpetic neuralgia.
  • Steroid therapy once was thought to decrease complications from shingles, but this has not been shown to help and may, instead, decrease the immune system/infection fighting ability of the system and put the patient more at risk.
  •  If older than 60, get herpes shingles vaccine.

Hope this helps!

Posted in General Medicine- Adults, infections, Uncategorized | Tagged , , , , , , , , , , , , | Comments Off on What to do if you think you have shingles. . .